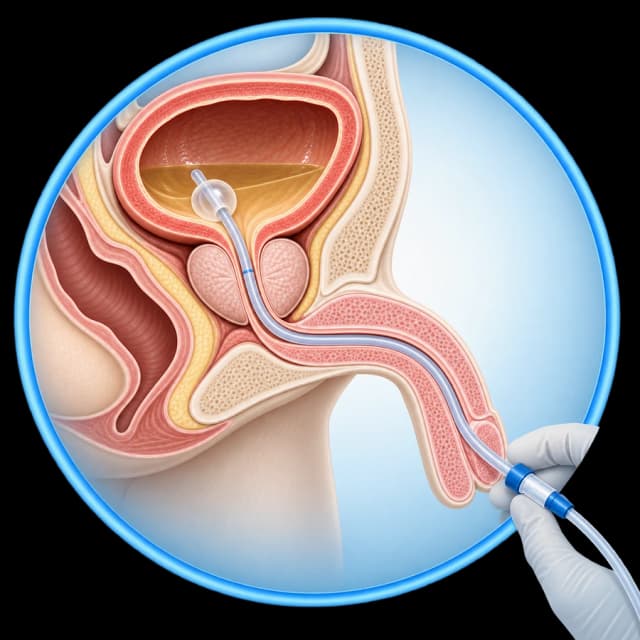
My Clinical Approach
A stone in the bladder is rarely an “isolated” finding without a cause. Particularly in adult men, it may reflect underlying obstruction, neurogenic dysfunction, a chronic catheter, or another anatomical/functional disorder.
My approach does not stop at removing the stone. It includes systematic investigation of the cause, so that treatment genuinely reduces the risk of recurrence rather than only addressing the current finding.
- Laser cystolithotripsy is not the same as RIRS, ureteroscopy, PCNL, or ESWL.
- It does not by itself address the cause of stone formation.
- Not every patient needs simultaneous prostate surgery.
- A high-power laser does not mean more Watts automatically produce a better outcome.
What Is Laser Cystolithotripsy
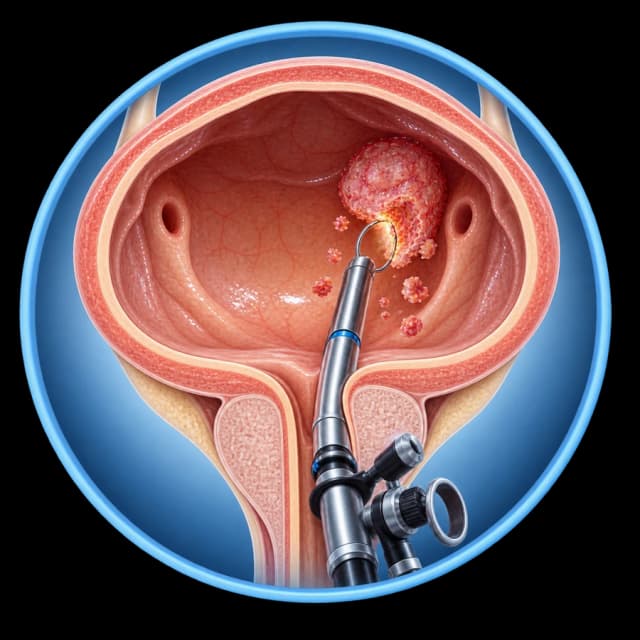
Laser cystolithotripsy is an endoscopic procedure in which a bladder stone is approached through the urethra, fragmented with a laser, and the fragments are removed from the bladder.
Removing the stone does not guarantee it will never form again.
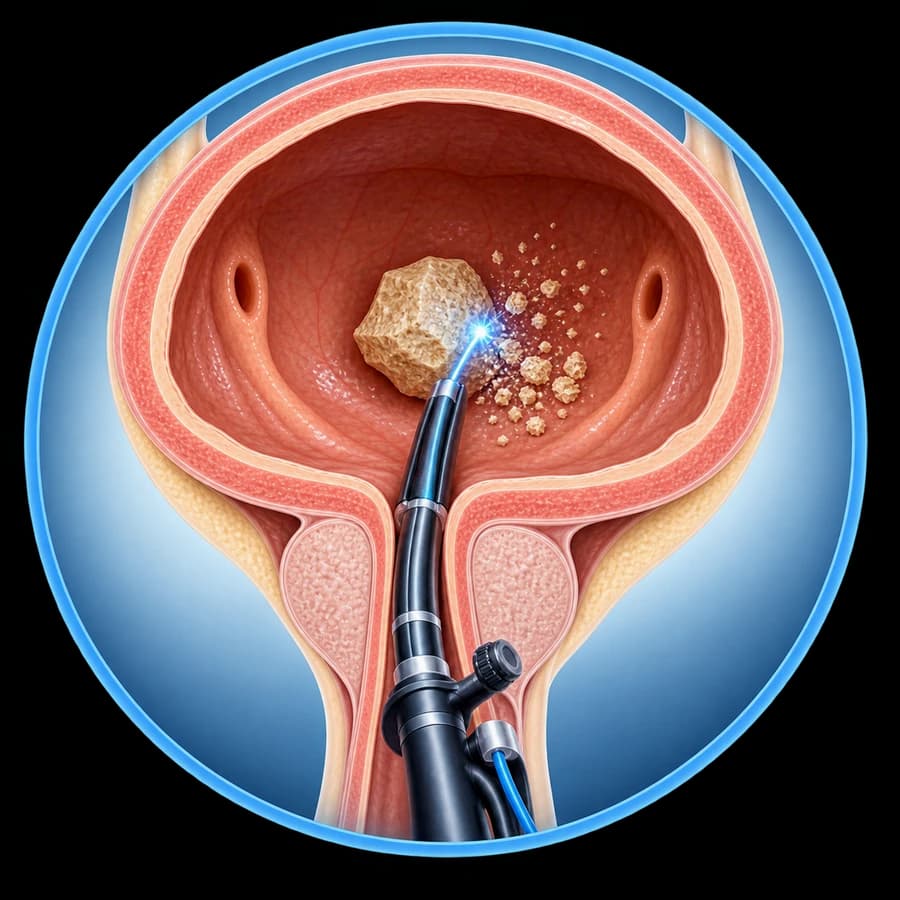
“It Is Not Enough to Remove the Stone – We Must Find Why It Formed”
Particularly in adult men, bladder stones may be related to:
BPH should not be presented as the only cause.
Bladder Stone ≠ Kidney Stone
Kidney Stone
Forms in the kidney.
Ureteral Stone
Located in the ureter.
Bladder Stone
Located in the urinary bladder and may have a different aetiology.
Some bladder stones form locally (e.g. due to obstruction or stasis), while others may have descended from the upper urinary tract.
Laser Cystolithotripsy ≠ RIRS
RIRS
Retrograde flexible ureterorenoscopy, for kidney stones, with access through the ureter into the kidney.
Laser Cystolithotripsy
Bladder stone, cystoscopic/transurethral approach, treatment inside the bladder.
See the page on Laser Kidney Stone Lithotripsy (RIRS) for kidney stones.
Laser Cystolithotripsy ≠ Ureteroscopy
Ureteroscopy treats ureteral pathology/stones. Cystolithotripsy treats stones inside the urinary bladder.
See the page on Endoscopic Ureteral Lithotripsy for ureteral stones.
Laser Cystolithotripsy ≠ PCNL
PCNL
Percutaneous renal access, mainly for large/complex kidney stones.
Cystolithotripsy
Treatment within the urinary bladder.
PCNL equipment/technique should not be confused with bladder-stone equipment.
Laser ≠ ESWL
Laser
Intracorporeal fragmentation under direct endoscopic vision.
ESWL
Extracorporeal shock waves generated outside the body.
Laser lithotripsy should not be called “shock-wave treatment”.
High-Power Holmium:YAG Laser
A high-power Holmium:YAG laser is available at Lefkos Stavros for endourological applications, including laser cystolithotripsy.
No specific wattage, manufacturer, model, pulse technology (e.g. Moses), frequency, or pulse energy is stated here, as these are not confirmed information for publication on this page.
What “High-Power” Means
“High-power” refers to the power/capability range of the laser platform.
It does not mean:
- •That maximum power is always applied
- •That more Watts automatically produce a better outcome
- •That every bladder stone requires a high-power setting
- •That it guarantees one-session treatment
The Holmium:YAG Laser
The Holmium:YAG laser can fragment urinary stones under direct endoscopic vision.
Depending on:
the stone is fragmented into pieces that can be removed.
Holmium ≠ Thulium Fiber Laser (TFL)
Holmium:YAG is an established, widely available laser technology in lithotripsy. The Thulium Fiber Laser (TFL) is a different technology, with different physical characteristics. Neither technology is presented here as universally superior – at Lefkos Stavros the confirmed available system is the high-power Holmium:YAG laser.
How the Procedure Is Performed
Anaesthesia
Appropriate anaesthesia is administered.
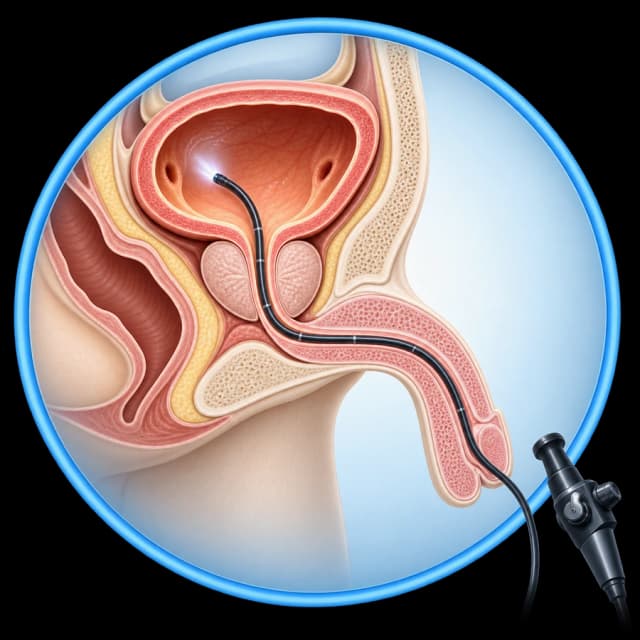
Endoscopic access through the urethra
No external incision in the typical approach.
Inspection of the urethra/bladder
Assessment before the procedure.
Identification of the stone(s)
Documentation of number/size.
Laser fragmentation
Under direct endoscopic vision.
Removal/evacuation of fragments
Removal of the fragments.
Assessment of the bladder
Confirmation of clearance.
Catheter placement where indicated
Depending on the procedure.
No Joules, Hz, power settings, fibre diameter, pulse width, “best” settings, fragmentation technique, endoscope handling, or irrigation pressures are given here — these are exclusively for the surgical team.
Anaesthesia
Cystolithotripsy is usually performed under appropriate anaesthesia, general or spinal/regional, depending on the patient, the stone, any simultaneous procedure, and anaesthetic assessment. Local anaesthesia alone is not always promised.
When Does a Bladder Stone Need to Be Removed
Possible reasons for indicated removal:
Not every tiny incidental stone necessarily needs the same management — asymptomatic, migratory stones may sometimes be monitored.
Symptoms
Symptoms are not diagnostic by themselves — it may also be an incidental finding.
Diagnosis
Bladder stones may be identified with:
No single test should be presented as mandatory for everyone.
Ultrasound vs Cystoscopy
Ultrasound
May demonstrate the stone, bladder volume, post-void residual, and sometimes associated abnormalities.
Cystoscopy
Directly confirms the intravesical stone and assesses the urethra, bladder neck, prostate, mucosa, foreign body, diverticulum.
Flexible cystoscopy is not mandatory in every case.
Why Did the Bladder Stone Form
Possible mechanisms:
Without treating the underlying cause, recurrence may remain possible.
Benign Prostatic Hyperplasia & Bladder Outlet Obstruction
In adult men, bladder outlet obstruction is the most common predisposing factor for secondary bladder stones. Assessment may include, as clinically appropriate:
It is not implied that every bladder stone requires prostate surgery. Urodynamic studies in men with bladder stones show that not all have documented obstruction — some have a normal study or an overactive bladder. See the page on Benign Prostatic Hyperplasia.
Can the Prostate Also Be Treated in the Same Surgery?
In appropriately selected patients with a bladder stone and clinically relevant bladder outlet obstruction/BPH, simultaneous surgical management may be considered.
Possible procedures, depending on the patient and available techniques, may include:
Not every patient with a bladder stone needs simultaneous prostate surgery. Large series show that simultaneous treatment of the stone and obstruction does not significantly increase major complications compared with obstruction surgery alone, although it may transiently increase early incontinence or urinary tract infection risk, according to current EAU guidance. The decision is individualised.
HoLEP & Cystolithotripsy
In selected men with significant bladder outlet obstruction and a bladder stone, stone treatment and surgical treatment of the obstruction can sometimes be combined in the same session. This does not mean that simultaneous treatment is universally suitable for everyone — it depends on anatomy, prostate size, stone burden, and the patient’s general condition.
Urethral Stricture
A urethral stricture may contribute to incomplete bladder emptying and complicate transurethral access during the procedure.
Management is individualised. Dilation or urethrotomy technique is not described here.
Neurogenic Bladder
Bladder stones occur more often in selected patients with neurogenic lower urinary tract dysfunction, chronic catheterisation, or impaired emptying.
Recurrence prevention may require management of the underlying bladder dysfunction, not just stone removal.
Chronic Catheter
Long-term catheterisation can be associated with:
Not all catheterised patients develop stones.
Foreign Body
Possible nidus:
No speculation about individual causes is made here.
Bladder Diverticulum
Urinary stasis within a bladder diverticulum can contribute to stone formation.
Treatment strategy depends on the diverticulum, obstruction, symptoms, and stone characteristics. Not every diverticulum needs surgery.
Recurrent Urinary Tract Infections
A stone may contribute to recurrent infection in selected cases.
Bacteriuria ≠ necessarily symptomatic UTI. Infection should be clinically assessed — no empirical antibiotic protocol is given here.
Stone + Fever / Sepsis
Fever, chills, poor general condition, or signs of systemic infection in a patient with obstruction/a stone require prompt medical assessment.
Size Is Not the Only Factor
Simplistic rules such as “<2 cm laser” or “>2 cm open surgery” are avoided. Treatment also depends on:
Large Bladder Stones
Large, very hard, or multiple stones may require longer endoscopic fragmentation, a different endoscopic approach, staged treatment, a percutaneous approach, or rarely open surgery, depending on the circumstances. Transurethral laser treatment is not presented here as always optimal.
Transurethral vs Percutaneous Approach
Transurethral
Natural orifice, no suprapubic access, common approach in adults. According to current EAU guidance, usually associated with shorter hospital stay, less pain, and shorter convalescence than the percutaneous approach.
Percutaneous
Suprapubic tract, useful when transurethral access is not feasible or not advisable.
There is no universally “better” method for every patient.
Open Cystolithotomy
Open removal now has a more selected role, but may still be considered for a very large stone burden, particular anatomy, concomitant open surgery, or other selected circumstances, according to current EAU guidance. It is not characterised here as obsolete.
Laser vs Other Lithotripsy Modalities
Various intracorporeal lithotripsy methods exist (mechanical, pneumatic, ultrasonic, laser). Laser offers precise fragmentation under direct vision. According to current EAU guidance, the available modalities appear similarly effective in terms of stone-free rate, although high-power lasers appear to reduce lithotripsy time. No modality is presented here as universally superior.
Stone Fragments
The goal is not simply to “dust” and leave clinically relevant fragments behind. Fragments are generally evacuated/removed as appropriate. Basket/evacuation technique is not described here.
Complete Stone Clearance
It does not promise 100% clearance, a single session, or zero residual fragments in every case. A large or multiple stone burden may sometimes require staged management.
Why the Stone Should Be Analysed
When stone material is available, composition analysis can help identify:
According to current EAU guidance, analysis is particularly recommended for first-time stone formers and in recurrence.
Metabolic Evaluation
Bladder stones are not always purely mechanical in origin. Depending on the patient/history, evaluation may include:
A single mandatory panel is not presented unless supported by current guidance.
Stone Composition
Possible types may include:
Composition is not assigned from appearance alone — laboratory analysis is required.
Uric Acid Stones
Some uric-acid stones may be amenable to urinary alkalinisation under medical supervision, in carefully selected circumstances. No self-treatment dosing is given here, nor is it implied that every bladder stone can be dissolved medically.
Do I Need a Catheter After Laser Cystolithotripsy?
A catheter may be placed depending on urethral manipulation, bleeding, bladder irritation, any simultaneous prostate procedure, and urinary retention risk. It is not mandatory for every patient.
How Long Does the Catheter Stay
There is no universal duration. It depends on the extent of the procedure, haematuria, voiding function, any simultaneous prostate surgery, and complications.
Hospital Stay
Same-day discharge is not universally promised. It depends on anaesthesia, stone burden, haematuria, the catheter, any simultaneous procedure, and comorbidities. Selected uncomplicated cases may have a short admission.
Recovery After Laser Cystolithotripsy
Most uncomplicated patients recover relatively quickly, but a universal timeline is avoided.
Return to Work
No rigid number of days is given. It depends on the extent of the procedure, the catheter, any simultaneous prostate surgery, occupation, and symptoms.
Hydration
Appropriate hydration is recommended according to general health, renal/cardiac status, and physician instructions. No universal “drink 3 litres” target is given here.
Bleeding
Small transient haematuria may occur.
Persistent heavy bleeding, clots, or urinary retention need assessment.
Infection
A possible complication. Fever, chills, or systemic deterioration should not be considered normal. Routine antibiotics are not given to everyone unless supported by current protocol.
Urethral Injury / Stricture
Transurethral instrumentation can rarely be associated with urethral trauma and subsequent narrowing. Risk depends on the context. Unsupported percentages are not used here.
Bladder Injury
Rare injury/perforation is included in the complication list. A surgical-management algorithm is not given here.
Urinary Retention
This can occur postoperatively, particularly with pre-existing obstruction, prostate enlargement, urethral pathology, oedema, clot retention, or bladder dysfunction.
Prompt assessment is needed if unable to void. See also the page on Urinary Retention.
Possible Complications
No unsupported complication percentages are used here.
Red Flags
Seek prompt medical assessment for:
- •Fever
- •Chills
- •Inability to urinate
- •Severe/worsening suprapubic pain
- •Persistent significant bleeding
- •Large clots
- •Vomiting/systemic deterioration
- •A catheter not draining, if one is present
Anticoagulants & Antiplatelets
Patients should not stop anticoagulants or antiplatelets on their own.
Management depends on the medication, indication, bleeding risk, the planned procedure, and any simultaneous prostate surgery. No universal stopping intervals are given here.
Urine Culture & Infection Control
Before elective endoscopic treatment, urine assessment may be appropriate based on symptoms, history, a catheter, infection risk, and current guidance. Clinically significant infection should be treated appropriately before elective surgery. No drug/dose instructions are given here.
Cystolithotripsy & Flexible Cystoscopy
Flexible Cystoscopy
Diagnostic inspection.
Laser Cystolithotripsy
Operative stone fragmentation/removal.
See the page on Flexible Cystoscopy.
Cystolithotripsy & TURBT
TURBT
Resection of a bladder tumour.
Cystolithotripsy
Fragmentation of a bladder stone.
If a suspicious bladder lesion is discovered during evaluation, it should follow the appropriate oncological pathway — see the page on TURBT.
The Patient Journey
Urinary Symptoms / Haematuria / Recurrent UTI / Incidental Finding
Initial clinical indication.
Ultrasound ± Cystoscopy ± Other Imaging
Initial work-up.
Bladder Stone Confirmed
The finding.
Why Did It Form?
BPH/obstruction · urethral stricture · bladder dysfunction · catheter/foreign body · diverticulum · infection · migratory stone · metabolic factors.
Is Active Stone Treatment Required?
The key decision.
Laser Cystolithotripsy in Selected Cases
Endoscopic treatment.
Fragmentation + Fragment Removal
The procedure itself.
Stone Analysis
Determination of composition.
Treat the Underlying Cause Where Indicated
E.g. obstruction, dysfunction, catheter.
Recurrence Prevention / Follow-Up
Final step.
This is an informational diagram, not a strict diagnostic/treatment algorithm — each case is discussed individually with the treating urologist.
Frequently Asked Questions (FAQ)
What is laser cystolithotripsy?
It is an endoscopic procedure in which a bladder stone is approached through the urethra, fragmented with a laser, and the fragments are removed from the bladder.
How does a bladder stone form?
Most commonly due to bladder outlet obstruction (e.g. benign prostatic hyperplasia), neurogenic bladder dysfunction, a chronic catheter or foreign body, urethral stricture, a diverticulum, infection, or migration of a stone from the upper urinary tract. Metabolic factors may also coexist.
How is the procedure performed?
Under anaesthesia, an endoscope is introduced through the urethra into the bladder, the stone is identified, fragmented with a laser, and the fragments are removed/evacuated. This is followed by inspection of the bladder and catheter placement where indicated.
Does it require an external incision?
Not in the typical transurethral approach. In selected cases with a very large stone burden or difficult access, a percutaneous or, rarely, an open approach may be needed.
What laser is used?
A high-power Holmium:YAG laser is available at Lefkos Stavros for endourological applications for stone fragmentation, including bladder stones.
What is the Holmium:YAG laser?
It is a laser technology that can fragment urinary stones under direct endoscopic vision. Depending on stone composition, size, hardness, anatomy, and surgical strategy, the stone is fragmented into pieces that can be removed.
What does high-power laser mean?
It refers to the power/capability range of the laser platform. It does not mean maximum power is always applied, that every bladder stone requires a high-power setting, or that it guarantees one-session treatment.
Is more Watts always better?
Not necessarily. Outcome depends on stone characteristics, anatomy, technique, equipment, surgeon experience, and treatment of the underlying cause — not only on laser power.
Do I need general anaesthesia?
General or spinal/regional anaesthesia is usually used, depending on the patient, the stone, and any planned simultaneous procedure. Local anaesthesia alone is not always the case.
Do I need a catheter?
A catheter is often placed, depending on urethral manipulation, bleeding, bladder irritation, any simultaneous prostate procedure, and urinary retention risk. It is not needed for every patient.
How long does the catheter stay?
There is no universal duration. It depends on the extent of the procedure, haematuria, voiding function, any simultaneous prostate surgery, and complications.
Do I need to stay in hospital?
It depends on anaesthesia, stone burden, bleeding, the catheter, any simultaneous procedure, and general health. Selected uncomplicated cases may have a short admission.
Is a little blood afterwards normal?
Mild, transient haematuria can occur. Heavy or persistent bleeding, clots, or inability to urinate need assessment.
What are the complications?
Transient dysuria, haematuria, urinary tract infection, urinary retention, urethral injury, later urethral stricture, bladder injury, residual stone, need for a further procedure, and anaesthetic complications.
Can the stone come back?
Yes, particularly if the underlying cause is not addressed (e.g. obstruction, neurogenic dysfunction, catheter, diverticulum). Without addressing the cause, recurrence remains possible.
Does the stone need to be analysed?
Yes, particularly in first-time stone formers, in recurrence under pharmacological prevention, or in early/late recurrence after complete removal. Analysis helps identify the stone type and appropriate prevention.
Why do bladder stones form in men with BPH?
Bladder outlet obstruction due to BPH is the most common cause of secondary bladder stones in adults, leading to incomplete emptying and urinary stasis. However, not every man with a bladder stone has clinically significant obstruction.
Will the prostate also need surgery?
Not automatically. If clinically significant obstruction is documented, simultaneous or staged treatment may be considered. Selected patients are initially monitored with medication.
Can it be done together with HoLEP or TURiS?
In selected patients, yes — large series show that simultaneous treatment of the stone and obstruction does not significantly increase major complications, although it may transiently increase early incontinence or urinary tract infection risk. The decision is individualised.
What is the difference between a bladder stone and a kidney stone?
A kidney stone forms in the kidney, a ureteral stone is located in the ureter, while a bladder stone is located in the urinary bladder and often has a different cause (obstruction, stasis, foreign body), although it can also result from migration of an upper urinary tract stone.
What is the difference between RIRS and cystolithotripsy?
RIRS is retrograde endoscopic surgery inside the kidney using a flexible ureterorenoscope, for kidney stones. Laser cystolithotripsy treats stones inside the urinary bladder using a cystoscopic approach.
Can a very large stone be treated endoscopically?
Many large stones can be treated endoscopically, but they may require more time, staged treatment, or an alternative approach (percutaneous or, rarely, open), depending on size, number, and hardness.
When is a percutaneous or open approach needed?
When a transurethral approach is not feasible or advisable (e.g. severe urethral stricture), or with a very large stone burden, according to current EAU guidance.
When should I contact a doctor urgently after the procedure?
With fever, chills, inability to urinate, heavy or persistent bleeding, large clots, or vomiting/systemic deterioration.
Related Topics
Book an Appointment in Rhodes
Treatment of a bladder stone is not always complete once it is removed. Investigating the cause — such as prostatic obstruction, incomplete bladder emptying, urethral stricture, or another functional/anatomical disorder — is important to reduce the risk of recurrence.
References & Sources
- EAU Guidelines on Urolithiasis, Chapter 6: Bladder Stones (2026) — uroweb.org
- EAU Guidelines on Management of Non-Neurogenic Male LUTS/BPO — uroweb.org
- EAU Guidelines on Urological Infections — uroweb.org
- Bschleipfer T, et al. Bladder stones: aetiology and treatment. EAU Urolithiasis Guidelines evidence base.
Medical Review

Medically reviewed by Dr. Marinos Vasilas – Urologist – Andrologist
Dr. Marinos Vasilas performs laser cystolithotripsy for bladder stones in Rhodes, using a high-power Holmium:YAG laser, with emphasis on investigating and treating the underlying cause.
View full profileThis page is for informational purposes only and does not replace individualised medical examination. Not every bladder stone requires the same treatment. Size alone does not determine the approach. Not every patient needs prostate surgery. A high-power laser does not guarantee one-session treatment. No laser setting stated here is a patient instruction. Anticoagulants should not be stopped without medical advice. Fever, urinary retention, or heavy bleeding after the procedure require prompt medical assessment.